I read every paper twice. Once as the scientist building the models. Once
as the operator who used to decide which programs lived or died. Those two
readings rarely agree, and the disagreement is usually the interesting part.
Short entries, one paper at a time, with the part most summaries skip:
what it would take to matter outside the lab.
New entries most weeks. Follow along via
RSS or
LinkedIn.
#015 ·
Note
Design, make, know
VivoSim Labs × Chemveda Life Sciences · Release, Nov 3, 2026 ·
GlobeNewswire release
Release record — VivoSim Labs × Chemveda Life Sciences, Nov 3, 2026. Headline, date, companies, and models as published, rendered as a bibliographic record (original typographic card, no release imagery reproduced) · Open the source ↗
In one line: On Nov 3, 2026, VivoSim Labs and Chemveda Life Sciences announced a collaboration to run AI-designed compounds through VivoSim's NAMkind Liver and Intestine models, built from primary human cells. Chemveda designs and synthesizes the molecules. VivoSim tests them. First programs are expected in Q4 2026. The performance numbers in the release are the company's own.
Takeaways
The loop is the story, not the models. AI can propose thousands of molecules. The bottleneck has been knowing which ones are safe in people. Here the test result reaches the chemist while the molecule can still change. Chemveda's line is "design-make-know" instead of "design-make-test." It is marketing, but the structure is real: a CRDMO offering that pairs synthesis with human-tissue data in one engagement. That is NAMs entering the service menu, not just the literature.
Read the performance numbers as company-reported. The release puts NAMkind Liver at 91 percent accuracy, 90 percent sensitivity, and 95 percent specificity for drug-induced liver injury, from a 92-compound clinical dataset, and says its screens can run more than 20 compounds in two weeks. No independent validation, no named customer, and no qualification milestone in the release. The numbers are a reason to ask for the data, not a reason to trust the model.
Check the scale. A Nov 13 write-up of VivoSim's Form 10-Q, filed Nov 12, puts quarterly service revenue at $51,000, with $22,000 of it from testing services, and about $8.6 million in cash at Sep 30. This collaboration is the bet on turning a platform into revenue. Watch for the first named program and the first customer data, not the next press release.
The bridge
Put this in front of a development program and the question is practical. A sponsor choosing a CRDMO for an AI-designed series now has an option that bundles synthesis with a human-tissue read before animal work. That changes the early decision: kill or redesign on human data, weeks in, instead of waiting for the animal package. The diligence questions stay the same: which compounds, which endpoints, and what did the model predict that the animal missed. Until a customer says so on the record, this is a credible offering for a real gap. It is not a validated platform.
Release record — VivoSim Labs, Nov 5, 2026. Headline, date, speaker, and the FDA rule as published, rendered as a bibliographic record (original typographic card, no release imagery reproduced) · Open the source ↗
In one line: On Nov 5, 2026, VivoSim Labs Executive Chairman Keith Murphy called on FDA to go further than its Sep 21, 2026 rule and treat some NAMs as already well-qualified. His ask is immediate proactive FDA review of use cases with enough credibility, then guidance that expects that data in IND filings, with an allowance for equivalent data, the same allowance animal studies get. His example is complex primary 3D liver models that caught liver toxicity animals missed. The argument is serious. The evidence behind it is his company's word.
Takeaways
The case is about the evidence bar, not the technology. Murphy's point is that FDA already gives a negative animal result real weight without demanding years of qualification first, and he wants the same for a negative result from a human model with reasonable qualification data. That asymmetry is the whole argument, and it is the same decision-ready question at the center of Dan's NAMs Opinion. Whether the case holds depends on whether the liver data is as strong as he says it is. He frames it as ethics, not just efficiency: "not requiring them or similar data is no longer ethically justifiable."
Read the liver claims as company-reported. The release names no compounds, no numbers, and no dataset. "Few false positives" and animals "later backfitted to see a signal" are vivid, but they cannot be checked from this release. VivoSim sells liver tissue models, so the call would directly help its business. One qualification to that caution: in a separate Nov 3, 2026 release, VivoSim did put numbers on its NAMkind Liver model, 91 percent accuracy, 90 percent sensitivity, and 95 percent specificity for drug-induced liver injury. Those figures are not in this call, and they are still the company's own numbers.
This is the counterpoint to Field Notes #012. NCAC, covered Nov 3, builds the paperwork path: terminology, data standards, qualification navigation. Murphy says the wait itself is the harm. Every year spent qualifying is another year patients in trials are exposed to liver-toxic compounds. Both can be true. The infrastructure matters, and the timeline is a policy choice. The question for FDA is which use cases are ready now, and who decides.
The bridge
Put this in front of a development program and the question is practical. If FDA wrote an expectation for primary 3D liver data into IND guidance, sponsors would need that data or equivalent before first-in-human. That is a new line item in the nonclinical package, a new vendor decision, and a new timeline. It is also a commercial opening for whoever sells the models. The diligence question stays the same: which use cases, which data, and who verified it. Until FDA answers, this is advocacy from a vendor with a genuine point. It is not a policy change.
Release record — DropGenie, Oct 26, 2026. Headline, date, investors, and financing as published, rendered as a bibliographic record (original typographic card, no release imagery reproduced) · Open the source ↗
In one line: On Oct 26, 2026, DropGenie of Montreal and Boston announced $5 million in Seed+ financing to scale a microfluidic platform that shrinks gene-editing workflows down to primary patient cells. The company says it uses up to 100 times fewer cells and far less reagent than conventional workflows. The round is small. The investor list is the story.
Takeaways
Read the 100x figure as the company's claim, not a result. It comes from DropGenie's own release, with no independent data behind it, no named pharma partner, and no qualification or regulatory milestone attached. The same goes for the integrations at "major global pharma, biotech, and research organizations." No names, no evidence yet. The number is a reason to test the platform, not a reason to trust it.
The model matters more than the money. DropGenie sells the platform three ways: run it in your own lab, buy studies as a service, or join data partnerships that build standardised functional datasets from primary patient cells. That third leg is the bet. A standardised dataset, repeatable and big enough to train on, is worth more than a faster edit.
The signal is Merck Global Health Innovation Fund, not the $5 million. A strategic investor joining a Seed+ round is a vote for the data-partnership model, not just the instrument. BDC Thrive Venture Fund joins the board. And note what the release does not say: it names no lead investor. At this size, the right read is infrastructure to watch, not a platform bet on the scale of the October platform deals.
The bridge
Put this in front of a development program and the question is concrete. A chip or an organoid is only as good as the cells that go into it, and primary patient cells are scarce, variable, and hard to edit at scale. If DropGenie can produce the same functional dataset from the same kind of cells, twice, at a scale a program can actually use, that feeds the same decision-grade-data argument as chips, one step upstream. Cell supply and editing, before the model. The diligence question is the same as ever: which partner, which dataset, and what reproducibility data. Until those answers appear, this is a credible address for a real bottleneck. It is not a validated platform.
NAMs
AI
#012 ·
Note
The plumbing behind qualification
Critical Path Institute (C-Path) · Release, Oct 1, 2026 ·
C-Path release
Release record — Critical Path Institute, Oct 1, 2026. Headline, date, partners, and funding as published, rendered as a bibliographic record (original typographic card, no release imagery reproduced) · Open the source ↗
In one line: On Oct 1, 2026, three nonprofits launched the National Center to Accelerate Cures (NCAC) in Baltimore with $3 million in congressionally directed funding. Its job is to help NAMs developers build the regulatory-grade evidence packages FDA requires before formally accepting a tool. That is qualification infrastructure, not a new model.
Takeaways
The size tells the story. Compare this with Field Notes #010, the $8 million NIH-funded THRIVE facility at Southern Research, announced Oct 12, 2026. THRIVE tests whether models hold up against animal and human data. NCAC does not build a test facility. It sits in the existing Blackbird BioHub incubator and works the other half of the problem: language, data standards, and qualification navigation, through C-Path.
The first-year plans are the test, and none of them exist yet. The release lists three: support regulatory submissions of its first NAMs in high-priority areas, publish a shared terminology framework, and release an open data standard for NAMs regulatory submissions. No NAM has been submitted or qualified through NCAC. No terminology framework or data standard has been published. Judge this center when those documents land, not at launch.
Read the track-record claim as the partners' claim. The release says C-Path has guided more drug development tool qualifications through FDA than any other organization. That superlative is not independently verified here. The underlying gap is still real. The release itself notes that most NAMs developers lack the infrastructure, regulatory expertise, and resources to generate the validation data FDA requires. Small companies and academic labs feel that gap first.
The bridge
Put this in front of a development program and ask what decision it changes. A model that works in the lab is only half the bet. The other half is whether FDA will accept the evidence, in what format, and described in what terms. If NCAC delivers common language and a data standard, reviewers can compare evidence packages more easily and sponsors waste less time translating between formats. If it only convenes meetings, it adds another logo to a slide. The diligence question is concrete: which submission, which terminology draft, which data standard, and by when. Until those appear, this is a credible address for a known bottleneck. It is not a qualification milestone.
Paper record, Logun et al., Cell Stem Cell 32(2), Feb 2025. Title, authors, journal, DOI and PMID as indexed (PubMed, captured Nov 2026), rendered as an original typographic card, no paper figure reproduced · Open the source ↗
In one line: Penn researchers grew tumor organoids from six recurrent glioblastoma patients and treated them with the same CAR-T product the patients received, in parallel. The organoids tracked the patients. That timing is what makes this paper different.
Takeaways
The design is the result. Most tumor organoid work is retrospective. This was not. Tissue came from surgical debulking in a phase 1 trial of dual-target EGFR-IL13Rα2 CAR-T cells (NCT05168423), and all six patients' organoids were ready within 2 to 3 weeks, inside the window between surgery and treatment. The organoids were then dosed with the same autologous CAR-T product, on the same timeline as the patients.
Two readouts moved with the clinic. The degree of tumor cell killing in the organoids correlated with CAR-T engraftment measured in patients' cerebrospinal fluid. Cytokine release patterns in the organoids mirrored the patients' cerebrospinal fluid samples over time. For a brain tumor you cannot biopsy repeatedly, and where MRI cannot always separate tumor growth from treatment inflammation, a contemporaneous lab readout has real value.
Read the limits plainly. Six patients, one phase 1 trial, one product. Correlation with patient measurements is not a validated diagnostic, and it says nothing about survival. The trial's own interim picture included tumor regression in all six patients within a month, but responses were not durable in all of them. This paper earns the organoid a role as a correlative readout. It does not earn it a role in picking who gets treated.
The bridge
Put this in front of a cell therapy program and ask what decision it changes. An avatar that only confirms what the clinic already showed is a nice poster. An avatar that reads bioactivity while the patient is still on treatment, before MRI settles the question, could change a dose call or a go/no-go on the next cohort. That is the bar to clear. It needs a prespecified readout, not a post hoc correlation. It needs the same assay to give the same answer at a second site. And it needs to survive its own logistics: an autologous product plus an autologous avatar doubles the manufacturing and handling chain, so the readout has to be worth the added failure points. Until a sponsor defines the decision the organoid gates, this stays a strong correlative tool, not a selection criterion. The distinction matters in diligence. Buy the correlation. Do not yet pay for the claim.
Release record — Southern Research, BusinessWire, Oct 12, 2026. Headline, date, and THRIVE expansion as published, rendered as a bibliographic record (original typographic card, no release imagery reproduced) · Open the source ↗
In one line: Southern Research won $8 million from NIH to build THRIVE, a national shared-use facility in Birmingham whose job is to test whether human-relevant models are actually ready for drug development. That is validation infrastructure, not a new platform claim.
Takeaways
Read the $8 million for what it is. The federal award listing (C06OD042705, $8.0 million, Sep 18, 2026 to Nov 30, 2030, under the NIH construction support program) funds the facility itself. It does not validate any model, and it does not come with validation data. The release gives no opening date, so treat THRIVE as infrastructure under construction, not a service you can book tomorrow.
The stated job is adjudication, and that is the point. THRIVE will work with collaborators on specific research and development needs and compare NAMs against existing animal and human data. That comparison is the missing step in most NAMs pitches. A model is not decision-ready because it looks human. It is decision-ready when it beats or matches the incumbent on a defined question, with data a regulator can inspect.
Shared use plus a commercialization neighbor is a deliberate pairing. NIH investigators, government researchers, and biotech and pharma companies all get access to the same models, data, and expertise. The facility sits steps from Station 41, Southern Research's commercialization hub, with its incubator, accelerator, and therapeutics fund. Validation and company formation on one campus means early companies can test against the same benchmarks their future partners and regulators will ask about.
The bridge
Read this the way you would diligence a validation claim. The right questions are not about the building. Ask what counts as ready: which comparator data, which acceptance criteria, and who signs off. Ask whether a result obtained at THRIVE travels, meaning the same model run elsewhere gives the same answer. Ask what decision the benchmark actually replaces: an animal study, a candidate kill, a clinical risk. Until THRIVE publishes benchmarks with those answers attached, this is a well aimed investment in the bottleneck, not proof the bottleneck is cleared. That distinction is the whole story. Field Notes #009 argued the multi-organ chip problem is manufacturing, not biology. THRIVE is the institutional version of that argument. The field does not mainly need more models. It needs a place whose job is to say which ones hold up.
NAMs
regulatory
#009 ·
Review
The multi-organ chip problem is manufacturing, not biology
Paper record — Li et al., Nat Biomed Eng 10(10), Oct 2026. Title, authors, journal, DOI and PMID as indexed (PubMed, captured Oct 2026) · Open the source ↗
In one line: A Stanford Review maps what it takes to make linked human organ chips predict drug ADMET, and its blunt point is that translation-ready systems are still out of reach. The biology is largely understood. Reproducibility is not.
Takeaways
ADMET is a system property, not a single-organ readout. A drug can look safe in an isolated liver culture and turn toxic only after gut absorption, liver metabolism, and kidney clearance act in sequence. That is why single-organ models, however good, cannot carry the prediction alone. The Review frames the body as a set of niches connected by selective exchange, and a chip has to preserve that structure to mean anything.
Two bottlenecks, both engineering. First, keep each organ's niche intact while letting organs talk: the right matrix, oxygen gradient, shear, motion, and barrier, plus endothelium that behaves like the organ it serves rather than generic pipe. Second, stop hand-building. Most devices today are low-throughput and hard to reproduce, which is fatal for a tool that has to produce comparable data across labs and lots.
Data is where this either pays off or misleads. Multimodal readouts, optical, electrical, biosensors, give the field the dense datasets AI workflows want. Liver organoid images already feed models that predict injury levels. But an AI model trained on irreproducible chip data just scales noise faster. Standardization comes before prediction, not after.
The bridge
Read this the way you would diligence a vendor. A multi-organ ADMET platform is not a demo of linked tissues. It is a manufacturing claim, a measurement claim, and a decision claim. Ask whether the same chip, run in two labs, gives the same answer. Ask whether the chip material itself soaks up your compound, because PDMS does, and that error lands straight in your pharmacokinetic read. Ask what decision the platform actually replaces: an animal study, a candidate kill, a clinical risk. Until a vendor answers all three, you have a roadmap with good engineering, not a decision tool. And keep the category straight. This is a Review. It maps the field and names the gaps. It does not validate any platform, and its ADMET output should not be read as validated human clinical prediction.
organ-on-chip
NAMs
AI
regulatory
#008 ·
Note
Zealand’s $30M bet, with a $1.2B ceiling
Zealand Pharma A/S and Generate Biomedicines · Company announcement No. 20 / 2026, Oct 13, 2026 ·
GlobeNewswire release
Header of Zealand Pharma’s company announcement No. 20 / 2026 — the release number, headline, and Oct 13, 2026 date. Company announcement via GlobeNewswire, captured Oct 2026 · Open the source ↗
In one line: Zealand paid Generate $30M upfront, with up to
$35M more tied to early preclinical milestones, to design multispecific
protein therapies for obesity with generative AI, while Zealand keeps the
clinic and worldwide commercial rights. The $1.2B is the announced milestone
ceiling, not committed cash. No candidate exists yet.
Takeaways
The structure, read like a diligence memo. Two programs to start, with an
option on a third. Generate owns the design loop through lead-candidate
selection, using what the release describes as generative AI plus
high-throughput experimental validation. Zealand takes everything after:
clinical development, regulatory submissions, worldwide commercialization.
The announced economics: $30M upfront, up to $35M in early preclinical
milestones, total milestones of nearly $1.2B plus tiered royalties. The
risk split is clean. Platform risk sits with Generate. Development risk
sits with Zealand.
The thesis is multispecifics for metabolic disease. One molecule built to
act on more than one target, aimed at several obesity-linked pathways at
once. Zealand’s roots are peptides; its petrelintide program with
Roche carries up to $5.3B in milestones. This deal reaches past peptides
into engineered proteins. The bet is that generative design, tested
experimentally at scale, can produce developable multispecifics faster
than traditional protein engineering. Discovery stage. No candidate, no
clinic, no drug yet.
It landed in a week of identical structures. Gilead and Vir signed Oct 14,
up to $1.88B, with Vir designing candidates on its dAIsY platform.
AstraZeneca and insitro signed Oct 15: $40M upfront, about $1.46B in
milestones, the Virtual Human platform aimed at MASH and cardiomyopathies,
AZ running the trials. Pfizer and Enodia, over $500M, with Enodia running
discovery and Pfizer taking the clinic. Same pattern in every one. Pharma
buys the design-to-candidate loop and keeps the clinic. When four BD teams
converge on one structure in a week, it is a market read, not a
coincidence.
The bridge
Read past the headline. In BD, the announced total is the ceiling. The
upfront and the near-term milestones are the bet. Here the bet is $65M: $30M
now, up to $35M tied to early preclinical gates. That is what Zealand was
willing to risk on generative protein design before a single candidate
exists. And look at where Zealand drew the handoff line. It bought discovery
and kept development. The platform company owns the design loop to candidate
selection. The pharma owns the clinic. Each side stays inside what it knows
how to do. For anyone diligencing an AI-discovery partnership, this is the
template to test against: who owns the design loop, who owns the clinic, and
how much of the headline number is actually committed before a candidate
exists. That is the diligence question. The rest is press release.
AI
#007 ·
Regulatory
Twenty-five times the FDA said yes to non-animal data
U.S. Food and Drug Administration · NAMs Database of Use Case Examples, launched September 2026 ·
FDA database page
Top of FDA’s NAMs Database of Use Case Examples page — the title, intro, and the Important Information box framing the 25 entries as illustrative, not guidance. “Content current as of: 09/18/2026.” Public FDA page, captured Oct 2026 · Open the source ↗
In one line: The FDA put 25 real review examples online
showing where non-animal methods were accepted in approved-drug applications.
Every one so far is a classic in-vitro tox endpoint: skin and eye
sensitization, irritation, corrosion. It is a precedent library, not a
permission slip.
Takeaways
The shape of the data. Twenty-five entries, organized by method, drawn from
public FDA review materials. “Content current as of: 09/18/2026.”
The methods: BCOP (10 entries), EpiSkin SIT (4), DPRA (3), h-CLAT (2),
KeratinoSens (2), Corrositex (2), U-SENS (1), EpiDerm SIT (1). The drugs read
like a recent approvals list: Symdeko, Veklury, Sunlenca, Cobenfy, Fabhalta,
Myqorzo, plus Twyneo, Filsuvez, Ojjaara, Zoryve, Sofdra, Zelsuvmi, Inluriyo,
Journavx.
The box that matters most. The page says it plainly: the list is
illustrative, not exhaustive, not FDA guidance, and not a promise that a
method will be accepted in another submission. Regulatory conclusions are
context-specific. Method, endpoint, product, data package, application. All
five have to line up. The page also points to the CAMERA database, the CDER
streamlined nonclinical studies page, and the March 2026 draft guidance on
NAMs in drug development. Read those before you cite the database in a
meeting.
Notice what is missing. No organ-on-chip. No organoids. No in-silico models.
Every entry is an in-vitro or in-chemico endpoint the industry has validated
for years. That is not a criticism. It is a map of where the agency’s
comfort zone ends today. The frontier has no precedent entries yet.
The bridge
Program teams do not ask whether NAMs work in principle. They ask whether this
method, for this endpoint, will survive a review. That is what makes this page
useful. For eight established endpoints, the answer is now a list of named
products you can cite in a Type D meeting. For everything else — chips,
organoids, in-silico — the answer is still a conversation you start
early, with a validation package the draft guidance describes and no precedent
entry to point at. The gap is the point. This table shows where the
agency’s comfort zone ends, and everything past that line is where the
qualification programs have to deliver. Watch for the first chip entry to
appear here. That will be the signal the frontier moved.
NAMs
regulatory
#006 ·
Paper
A spiral chip sorts tumor cells by size. A camera names them.
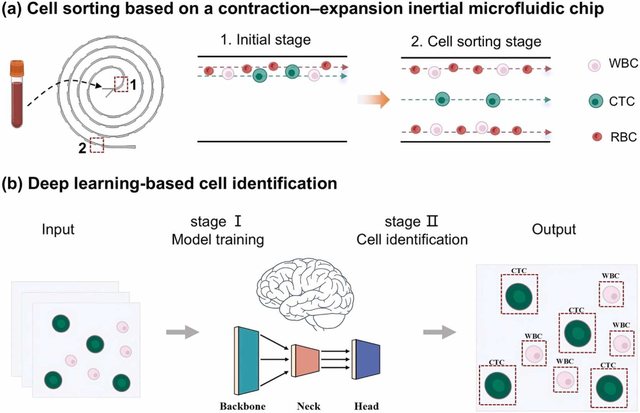
Figure 1 — Ouyang et al., Biomedical Analysis 3(3), Sep 2026: (a) the contraction–expansion spiral chip sorting CTCs from white and red blood cells by size; (b) the YOLOv8 pipeline identifying tumor cells from bright-field images. Full figure, resized; CC BY-NC-ND 4.0 · Open the source ↗
In one line: A spiral inertial chip with contraction–expansion
arrays pulls MCF-7 tumor cells out of spiked blood at 89.2% recovery while
clearing 86.9% of white blood cells, then a YOLOv8 model picks the tumor cells
out of plain bright-field images at 94.6% precision and recall. No antibodies.
No fluorescent stains.
Takeaways
The sorting is pure physics. Periodic contraction–expansion structures
inside a spiral channel combine inertial lift, Dean drag, and vortex-induced
lift to separate cells by size alone. That sidesteps the oldest weakness of
CTC capture: most methods fish with EpCAM antibodies, and tumor cells that
went through epithelial-to-mesenchymal transition shed EpCAM. Size is much
harder for a cell to fake. The whole enrichment stage is passive. No labels
to buy, no surface chemistry to maintain.
The identification step runs on a plain microscope image. Fluorescence was
used to annotate training data, but inference needs only bright-field. That
is the detail that matters operationally: unstained cells stay intact for
whatever comes next, single-cell sequencing or drug-susceptibility testing.
Most CTC pipelines stain the cells to find them and destroy the sample in
the process. This one keeps its options open.
Read it as a methods paper, not a diagnostic. The validation used MCF-7
cells spiked into artificial blood, not patient samples. The enrichment and
recognition halves are presented as one strategy but have not been run as
a single automated system. Proof of concept, honestly framed. The numbers
describe this cell line and this protocol. Nothing more.
The bridge
Rare-cell prep is the boring bottleneck in front of every elegant single-cell
assay. A passive, label-free front end that leaves cells alive and unstained
is exactly the kind of unglamorous hardware that makes functional testing on
real patient CTCs practical: enrich, image, then actually test drugs on the
cells instead of guessing from markers. What has to happen before this
matters outside the lab: patient blood, more tumor types than one breast
cancer line, and the two halves bolted into one automated box. Note the
fabrication angle too. Spiral channels and contraction–expansion
structures are standard soft lithography. No exotic materials, no clean-room
heroics. This is a chip a small team can actually build, which is precisely
why the design is worth more attention than the accuracy number.
Paper record — Reza et al., Nature 641(8065), May 2025. Title, authors, and DOI as indexed (PubMed, captured Oct 2026) · Open the source ↗
In one line: Takebe’s group built liver organoids
with the lobule’s zonal architecture baked in: periportal and
pericentral programs in the same system. They did it by preconditioning
stem-cell-derived progenitors with ascorbate and bilirubin, then showed
the organoids could keep rats alive after bile-duct ligation.
Takeaways
The trigger is almost embarrassingly simple. Progenitors enriched with
ascorbate or bilirubin, co-cultured, self-assemble into zonally
patterned organoids. Zone identity turns out to be epigenetic: EP300
binds TET1 or HIF1a depending on the cue. Engineer a little, let the
biology do the rest.
Function tracks the zones. Urea cycle, glutathione synthesis, and
glutamate synthesis show up in the right zones. That matters because
drug-metabolizing enzymes are zoned in a real liver too. A featureless
cell ball cannot answer a zonal toxicity question. This one can start
to.
The survival assay is functional proof, not a transplant product.
Transplanted into rats after bile duct ligation, the organoids cut
ammonia and bilirubin and improved survival. Nobody is putting these
into a human liver. That is fine. The model does not have to be a
therapy to be a better assay.
The bridge
Drug-induced liver injury is still one of the top reasons compounds die
late. And the field keeps asking uniform organoids zonal questions.
Zonation is exactly the kind of readout that makes a NAMs validation
package richer, same direction as the behavioromics entry two notes
back: richer assays, not just animal-free ones. The obvious next step
is a zoned organoid on a perfused chip, benchmarked against a blinded
drug panel the way the Emulate Liver-Chip was. Nobody has closed that
comparison yet.
liver organoids
drug metabolism
NAMs validation
#003 ·
Regulatory
The FDA just rewrote “animal” out of its rulebook
U.S. Food and Drug Administration · Direct final rule, Sep 22, 2026 ·
FDA NAMs page
FDA’s official NAMs page — the hub behind the Sep 22 direct final rule. Captured Oct 2026 · Open the source ↗
In one line: The FDA replaced “animal” with
“nonclinical” across its drug safety regulations, so organ chips
and computer models now count as legitimate safety testing before
first-in-human trials.
Takeaways
It is a terminology rule, not a new requirement: parts 312, 314, 315,
361, and 601 of 21 CFR now say “nonclinical” where they said
“animal.” Effective Feb 4, 2027, unless significant adverse
comments arrive by Dec 7, 2026.
The bar did not move. Sponsors must still show a drug is reasonably safe
before human trials. What changed is that a validated chip or model can
now be part of that showing, and sponsors can request feedback on a
specific NAM through a Type D meeting.
The quieter story: the FDA published a database of 25 real cases where
non-animal data was already accepted in past reviews. Precedent, in
writing, from the agency itself.
The bridge
I have sat in the sponsor’s seat. Policy does not move pipelines;
precedent and de-risked validation do. The 25-example database is the real
story here. It is the beginning of a qualification playbook. Anyone
building organ-on-chip platforms should be mapping their validation data
against those 25 cases right now, because that is exactly where the BD
conversations will happen next year.
NAMs
regulatory
#002 ·
Paper
Eighteen ways immune cells misbehave in sepsis, counted one cell at a time
Paper record — Brown et al., Science 392(6801), May 2026. Title, authors, and DOI as indexed (Europe PMC, captured Oct 2026) · Open the source ↗
In one line: They turned microscope movies of immune cells
into behavioral data, found 18 distinct behavior clusters during sepsis,
and showed an existing asthma drug can break up the dangerous ones.
Takeaways
The method is the headline: “cellular behavioromics.” Shape,
speed, and direction per cell, quantified and run through a
bioinformatics pipeline. Imaging treated as a data modality, not a
picture.
Heterogeneity is the story again. Eighteen behavior clusters in immune
swarms during sepsis, some protective and some pathogenic. Phenotype
first, molecule second.
In mice, a well-known asthma medication prevented the pathogenic
clustering. Same repurposing logic as my 2025 paper: match the
mechanism to the subgroup, then pick from the approved shelf.
The bridge
For industry, the drug hint is not the interesting part. The assay logic
is. If behavior is quantifiable, it is screenable. A microfluidic platform
that reads out 18 behavioral clusters instead of one viability number is
a far stronger validation tool for AI-predicted compounds. That is the
direction NAMs validation has to go: richer readouts, not just
animal-free ones.
sepsis
drug repurposing
AI
#001 ·
Note
Why I’m keeping field notes
In one line: Fourteen years deciding which drug programs
deserved funding, now building the assays those decisions depend on. This
log is where the two perspectives meet.
The bridge
Most paper summaries stop at what the authors found. I want to write down
the next question: what would it take for this to survive contact with a
real development program? Throughput, validation, cost, regulatory
precedent. If an entry here ever helps someone build that case, it did
its job.